
Introduction
Perimenopause and post-menopause are not only about hot flushes. They involve metabolic, bone, cardiovascular and other systemic changes that often begin years before periods stop — sometimes even when a woman still feels “fine.”
Understanding these changes early — and the evidence-based options available — allows women to make informed, confident decisions about their long-term health.
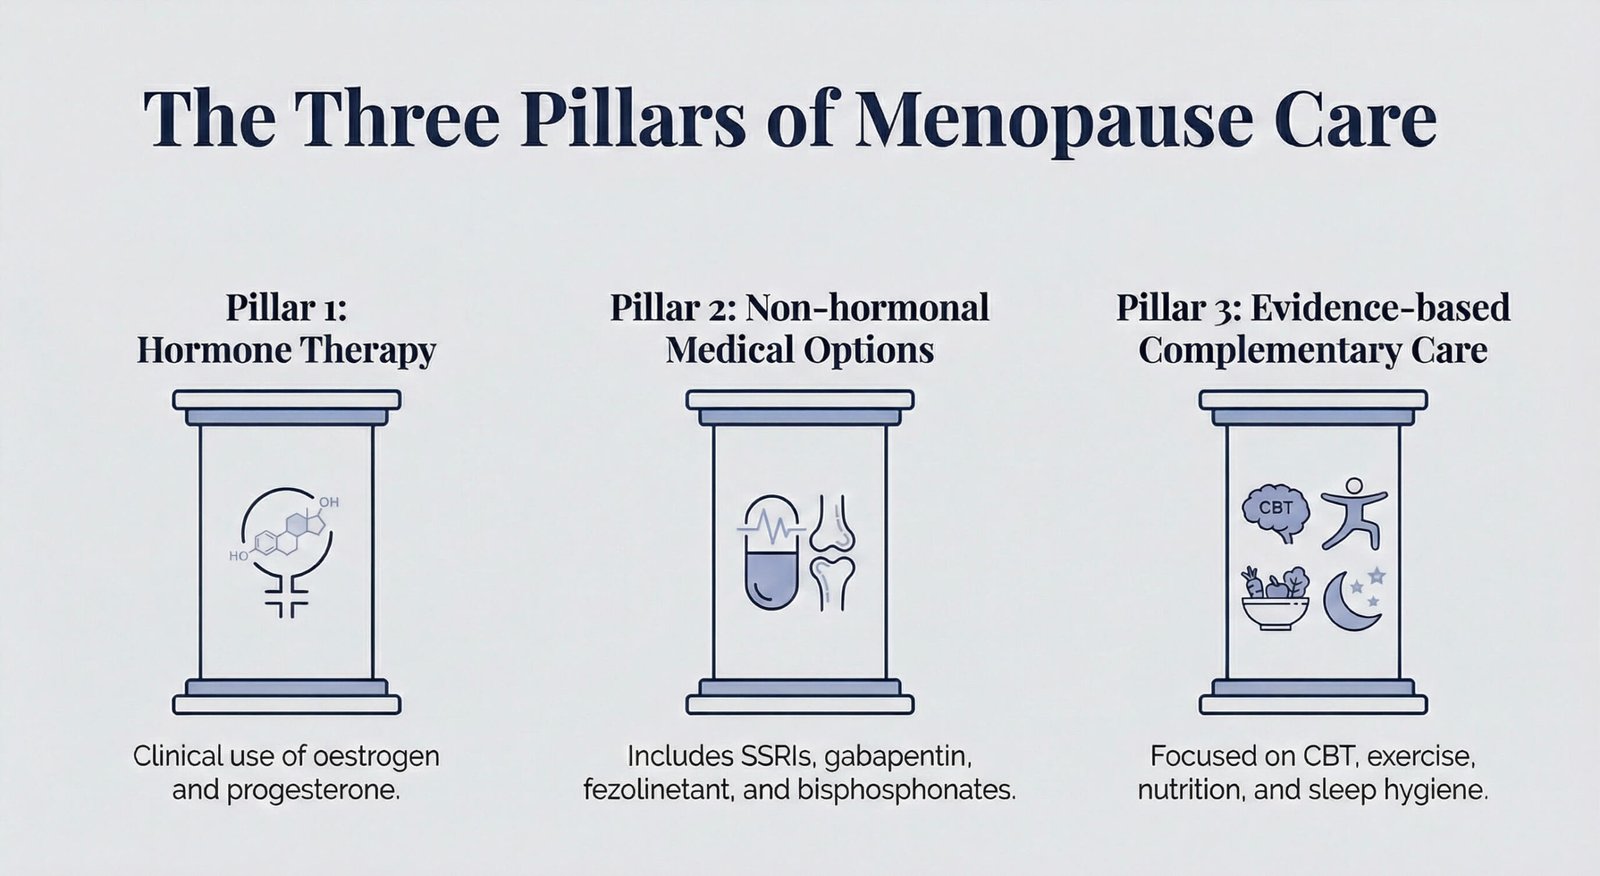
This article summarises the three essential pillars every woman should know. Each pillar is evidence-based, medically grounded, and aligned with international guidance (IMS, NICE, NAMS).
Your deeper guide is available in my book Menopause: The 3 Pillars Every Woman Should Know.
1. Perimenopause and Post-menopause -Hormonal Therapy
When It’s indicated and safe
Menopausal hormone therapy (MHT) replaces the oestrogen and progesterone your ovaries no longer produce.
For many women, MHT is the most effective tool for:
- Moderate to severe vasomotor symptoms (hot flushes, night sweats, sleep disruption)
- Genitourinary syndrome of menopause (vaginal dryness, painful sex, urinary symptoms)
- Prevention of osteoporosis
- Premature ovarian insufficiency (POI)
Why hormones matter
Oestrogen influences much more than symptoms: it supports bone formation, muscle function, glucose metabolism, blood vessels, cognition, pelvic tissues and other systems essential to health.
When levels fall, these systems shift — often rapidly — creating changes in fat distribution, bone density, mood and urinary health among others.
Types of hormonal therapy
Oestrogen may be given as transdermal patches or gel (preferred due to lower clot risk), oral formulations, or vaginal oestrogen for local symptoms.
Progesterone is usually added if a woman has a uterus, or in selected cases such as previous endometriosis, to protect any remaining endometrial tissue.
Micronised progesterone is closest to the progesterone your own body produces and is generally well tolerated.
Other synthetic progestins have additional actions – for example androgenic, anti-androgenic, glucocorticoid or mineralocorticoid effects – which can be helpful in some situations but may also increase side-effects.
Testosterone is not a routine menopause treatment, but in selected post-menopausal women it may be prescribed to treat hypoactive sexual desire disorder (HSDD) after proper clinical assessment. When indicated, it is used in physiological doses following international guidelines (IMS, NAMS, BMS).
Other hormonal options include low-dose vaginal oestrogen for genitourinary symptoms, tibolone (for selected women after menopause), and CEE combined with bazedoxifene, which pairs oestrogen with a SERM for endometrial protection.
Who should avoid MHT
International guidelines agree on key contraindications:
- History of breast cancer
- Active cardiovascular or thromboembolic disease
- Unexplained vaginal bleeding
- Pregnancy
- Oral oestrogen should be avoided in women with obesity, uncontrolled hypertension, high triglycerides, smoking or migraine with aura. In these cases, transdermal oestrogen is usually preferred and may be used safely.
2. Perimenopause and Post-menopause-Non-Hormonal Medical Options
In perimenopause and post-menopause not all women can or wish to use hormone therapy. In these cases, there are non-hormonal medicines with good evidence that can help.
For hot flushes and night sweats:
- Fezolinetant – a non-hormonal medication that acts in the brain (NK3-receptor antagonist) to reduce vasomotor symptoms.
- Certain antidepressants (such as venlafaxine, escitalopram or paroxetine) can reduce flushes and are recommended in guidelines when MHT is unsuitable.
- Gabapentin may help particularly with night sweats in some women.
For bone protection when osteoporosis is a concern:
- Bisphosphonates (such as alendronate or risedronate), denosumab or, in very high-risk cases, romosozumab can reduce fracture risk without using hormones. These are usually prescribed after a specialist assessment.
3. Perimenopause and Post-menopause – Complementary Therapies
Complementary therapies can be highly valuable when used alongside medical treatment — but they do not replace hormonal changes occurring at ovarian level.
• High-intensity resistance and impact training → can stimulate bone formation, improve muscle mass, and reduce fall risk. It is one of the most effective complementary strategies for bone health.
• Weight loss, reduce visceral fat and increase muscle → supports metabolic and cardiovascular health.
- Tailored nutrition → supports metabolism, muscle, weight and bone health.
- CBT → reduces hot flashes distress, sleep disturbance and anxiety.
- Yoga, mindfulness and meditation → beneficial for stress and overall wellbeing.
These methods complement the medical pillars, but cannot reverse bone loss, vasomotor instability or oestrogen-driven metabolic shifts on their own.
Medical support programme for healthy weight
Alternative therapies
Acupuncture, homeopathy, herbal mixes, “natural” hormone alternatives and unregulated supplements do not address the underlying hormonal changes in perimenopause or post-menopause, nor show clinical efficacy to reduce symptoms
Women relying exclusively on these approaches often reach their 50s–60s with osteoporosis or bone loss, and preventable metabolic, cardiovascular and genitourinary risks, among others.
Conclusion -putting the Three Pillars Together
Every woman’s needs are different. Some require hormonal therapy; others benefit from non-hormonal options; all benefit from a strong lifestyle foundation.
The key is choosing the right pillar at the right time, based on your symptoms, personal risks and long-term goals.
To go deeper into each pillar — with explanations, diagrams and clinical insights — you can read my book here
